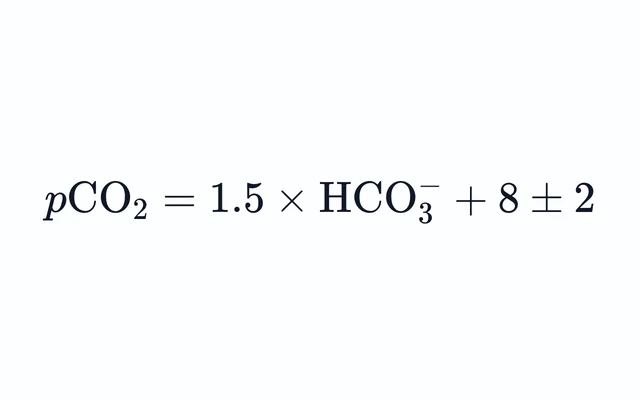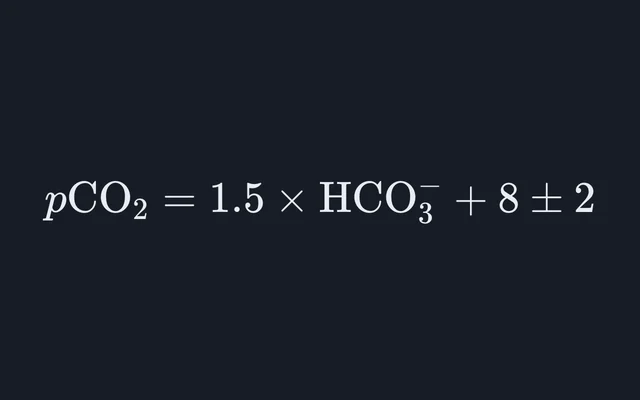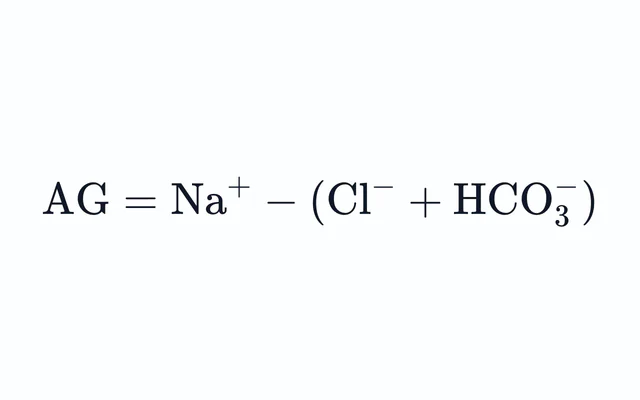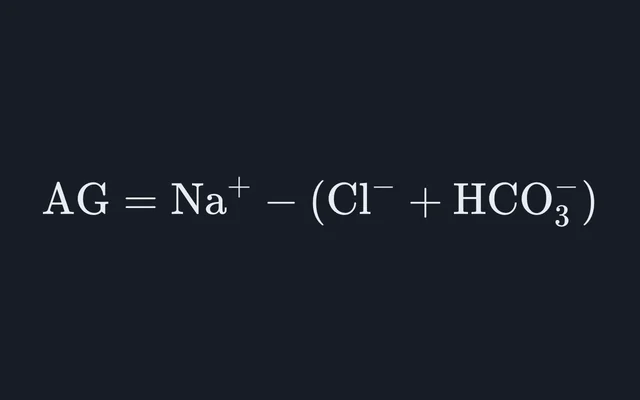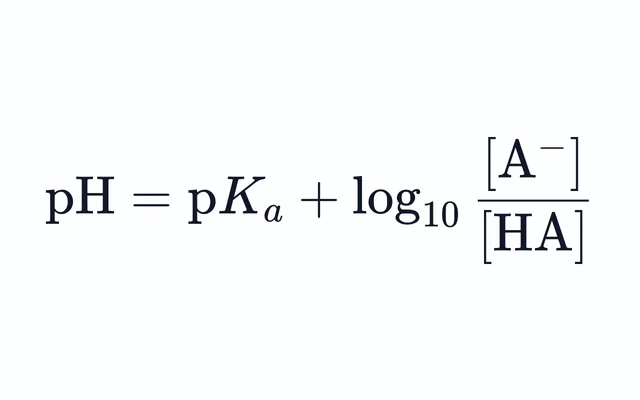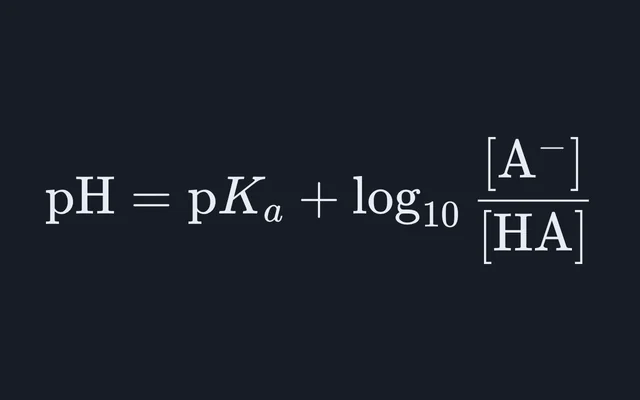Acid Base Interpreter
Enter a blood gas and work through the acid base diagnosis, with the anion gap, expected compensation and mixed disorders each shown as a stated step.
Calculator
Reference 7.35 to 7.45
Reference 35 to 45 mmHg
Reference 22 to 26
For the anion gap
For the anion gap
Corrects the gap. A low albumin hides a raised one.
- Primary disorder Of pCO2 and bicarbonate, whichever is deranged in the direction that produces this pH. A normal pH names none, because a normal pH is also what a fully compensated or a mixed picture looks like.
- metabolic acidosis
- pH Reference 7.35 to 7.45. This names the disturbance, not its cause.
- 7.1 acidemia
- Anion gap Na minus Cl minus HCO3, corrected for albumin. Reference 8 to 12. Raised means an unmeasured anion has been added.
- 30 mmol/L
- Compensation Whether the response matches the size this disorder alone would produce. Anything else is the evidence of a second disorder, and it is the whole reason to check.
- insufficient
- Delta ratio Rise in gap over fall in bicarbonate, interpretable only in a raised gap acidosis. About 1 for a pure one, below 1 if a normal gap acidosis coexists, above 2 if a metabolic alkalosis or chronic respiratory acidosis coexists.
- 1
- Reading Mixed whenever any step cannot be explained by the primary disorder on its own. With no primary disorder named it says only that the values are in range, or that they are compensated or mixed, since a normal pH can hide opposing disorders.
- mixed disorder
Working through it
pH 7.1, acidemia, so the pH is below the reference interval
This names the disturbance, not its cause. The next step decides which of the two variables explains it.
Primary metabolic acidosis
Of pCO2 and bicarbonate, this is the one deranged in the direction that produces the observed pH. pCO2 is 20 mmHg and bicarbonate is 6 mmol/L.
Compensation insufficient, expected 15.0 to 19.0 mmHg pCO2, measured 20.0 points to a second disorder
Winters’ formula, 1.5 x HCO3 + 8, plus or minus 2. Compensation outside every predicted band is the evidence that a second disorder is also present, because compensation for one disorder does not overshoot or fall short on its own.
Anion gap 30.0, corrected to 30.0 mmol/L, which is raised
Na minus Cl minus HCO3. A raised gap means an acid has been added whose anion the panel does not measure; a normal gap in an acidosis means bicarbonate was lost or chloride gained.
Delta ratio 1.00
Near 1, up to about 2, which is what a raised-gap acidosis on its own produces.
Cite this tool
Citing this tool
Last updated . Add the date you accessed it as well, which a citation of a page that can change asks for. If a specific result matters, cite the permalink from the tool’s share row instead of this page: it reproduces the exact parameters.
On the syllabus: MCAT, 3B: Structure and integrative functions of the main organ systems.
The equation
Henderson-Hasselbalch, with Albert, Dell and Winters (1967)
The equation as an image to reuse

How do you interpret an arterial blood gas (ABG)?
Read an arterial blood gas (ABG) in a fixed order. The pH (normal 7.35 to 7.45) names an acidemia or alkalemia. PaCO2 (normal 35 to 45 mmHg) tests for a respiratory cause and HCO3− (normal 22 to 26 mmol/L) for a metabolic one. Check that compensation is the expected size, then use the anion gap to classify a metabolic acidosis.
Read it in this order, every time
Each step depends on the one before it, and taking them out of order is how a mixed disorder gets read as a simple one.
- pH. Name the disturbance. Below 7.35 is an acidemia, above 7.45 an alkalemia. This says nothing about the cause.
- Which value explains it. An acidemia can only come from a raised
pCO2or a fallen bicarbonate. Whichever is deranged in the direction that lowers pH is the primary problem, and that decides respiratory or metabolic. - Is the compensation the right size? This is the step most often skipped, and it is the main way a second disorder shows itself.
- Anion gap. Only now, and only to narrow a metabolic acidosis.
- Delta ratio, if the gap is raised, to ask whether anything else is going on alongside it.
Why compensation stops short of a normal pH
The signal driving compensation is the pH disturbance itself. If the pH came all the way back to normal the stimulus would be gone and the response would stop, so the body settles at a partial correction. The one recognized exception is long-standing respiratory alkalosis, as at high altitude or in pregnancy, where renal compensation can bring the pH back into the normal range.
Outside that exception, a pH in the middle of the reference interval alongside a large primary disturbance is evidence of a second, opposing disorder.
Winters’ formula, and what it is for
Expected pCO2 = 1.5 × HCO3 + 8, plus or minus 2, in mmHg.
The formula checks whether the respiratory response to a metabolic acidosis is the size it
should be. A measured pCO2 above the predicted range means the patient is not
blowing off CO2 as they should, so a respiratory acidosis sits on top. Below the range, a
respiratory alkalosis is also present, the classic salicylate picture.
Winters’ formula applies to metabolic acidosis alone, and on an alkalosis its answer means
nothing. A metabolic alkalosis has its own rule, a rise of about 0.7 mmHg per
mmol/L of bicarbonate above 24, up to about 55 mmHg (Merck). Contrary to early
views, low oxygen does not stop that response: “neither hypoxemia nor potassium depletion
prevents expression of this response” (Adrogué and Madias). It can take 24 to 36 hours to
develop fully, so a gas drawn early may show less.
Acute and chronic are different rules for the same disorder
Renal compensation takes days, so the bicarbonate response to a given pCO2
depends on how long the disturbance has been present. In a respiratory acidosis bicarbonate
rises roughly 1 mmol/L per 10 mmHg acutely and about
4 mmol/L per 10 mmHg once compensation is established, a factor of
four. In a respiratory alkalosis it falls about 2 and then about 4 mmol/L per 10 mmHg (Merck
gives 4 to 5 once compensated). Every band is plus or minus 2, the tolerance Ayala-De la Cruz
and colleagues apply from Berend and colleagues and Rodríguez-Villar and colleagues.
A blood gas cannot tell you which applies, so this tool shows both bands and leaves the choice
to the history. The choice matters most for the chronic carbon dioxide retainer: a
pCO2 of 60 with a bicarbonate of 31 and a pH of 7.34 is appropriate chronic
compensation, and the acute rule would call it a metabolic alkalosis that does not exist.
The anion gap, and the albumin correction that gets forgotten
Anion gap = Na − Cl − HCO3. Charge balances exactly, so the gap is the anions the
panel does not report, less the cations it does not report. A raised gap means an acid has been
added whose anion is one of them, such as lactate or a ketoacid. A normal gap in an acidosis means
bicarbonate was lost or chloride gained instead, as in diarrhea or a renal tubular acidosis.
Albumin is the largest single contributor to the normal gap, because it carries net negative
charge at physiological pH. In hypoalbuminemia the baseline gap is therefore lower, and a
raised-gap acidosis can present with a gap that looks normal. The correction adds about
2.5 mmol/L for every 1 g/dL that albumin sits below 4.
A critically ill patient with an albumin of 2 and a lactic acidosis can show an uncorrected gap of 11, inside the reference interval. Corrected, it is 16, which changes the differential. Enter an albumin of 2 g/dL with a panel whose gap is 11 to see the reading change.
The delta ratio
(corrected gap − 12) / (24 − HCO3), and it is only interpretable in a raised-gap
acidosis.
In a pure raised-gap acidosis each bicarbonate consumed is replaced by one unmeasured anion, so the ratio is about 1. Well below 1 means bicarbonate fell further than the gap rose, which needs a second, normal-gap acidosis to explain. Above about 2 means the gap rose further than bicarbonate fell, which needs a coexisting metabolic alkalosis, or a chronic respiratory acidosis holding the bicarbonate up.
Its denominator vanishes as bicarbonate approaches normal, so the ratio explodes and stops meaning anything. The tool reports it as n/a when the gap is not raised or bicarbonate has fallen by less than 4 mmol/L, rather than printing a large number.
Check the gas is internally consistent first
pH, pCO2 and bicarbonate are not independent: Henderson-Hasselbalch fixes any one
from the other two. Catch a set that cannot coexist before you interpret it, since every later
step assumes the three agree.
The tool recomputes the pH from the other two and flags a disagreement above 0.05. A blood gas
analyzer measures the pH and pCO2 and calculates its bicarbonate from them with
Henderson-Hasselbalch (Merck), so figures copied from one printout agree. A disagreement means a transcription error, or a bicarbonate taken from a
chemistry panel drawn at a different time from the gas.
The same equation explains why a chronic retainer can have a nearly normal pH with a
pCO2 of 60. pH depends on the ratio of bicarbonate to dissolved CO2, and a
bicarbonate of 32 against a pCO2 of 60 gives 7.35, close to the 7.40 of 24
against 40. At exactly 7.35 the pH is inside the reference interval, so this tool names no
primary disorder and reads it as compensated or mixed.
What this tool leaves out
It sees six numbers. It knows nothing about the patient, the history, the drug chart, the lactate, the glucose, the ketones, or the osmolar gap. A raised anion gap narrows a differential and does not choose from it, and no arrangement of these six values can distinguish a ketoacidosis from a lactic acidosis from a toxic alcohol.
It also uses the bicarbonate and anion gap approach rather than the Stewart physicochemical approach, which may be more useful in critically ill patients with strong ion or weak acid disturbances (Ayala-De la Cruz and colleagues). The reference intervals here are typical teaching values, not any particular laboratory’s, so read a real report against the intervals printed on it.
Common mistakes
- Skipping the compensation step. It is the main way to find a second disorder. Naming the primary disturbance and stopping there gets the simple cases right and misses the mixed ones.
- Using Winters’ formula on an alkalosis. It is derived for metabolic acidosis alone.
- Judging a chronic retainer by the acute rule. It invents a metabolic alkalosis out of appropriate renal compensation.
- Forgetting the albumin correction. A low albumin hides a raised gap, and critically ill patients, who often have a low albumin, are also the ones likely to have a lactic acidosis.
- Reading a normal pH as normal acid base status. It is also what a fully compensated chronic respiratory alkalosis and two opposing disorders look like.
- Mixing up mmHg and kPa. 1 kPa is 7.5 mmHg, and every rule here is written in mmHg, so the tool makes the unit a visible choice.
- Expecting compensation to overshoot. The disturbance is what drives it, so it stops before the pH crosses normal. Apparent overshoot is a second disorder.
Sources
Ayala-De la Cruz S and colleagues, J Clin Med 2025;14:6676, for the compensation equations with their plus or minus 2 tolerance, from Berend K, de Vries APJ and Gans ROB, N Engl J Med 2014;371:1434-1445, and Rodríguez-Villar S and colleagues, Rev Esp Anestesiol Reanim 2020;67:20-34, and for the delta ratio bands. The Merck Manual Professional Edition’s Acid-Base Disorders page, for the 55 mmHg ceiling, the chronic respiratory alkalosis range, the albumin correction and the calculated bicarbonate. Adrogué HJ and Madias NE, Secondary responses to altered acid-base status: the rules of engagement, J Am Soc Nephrol 2010;21:920-923, for the 0.7 mmHg slope in metabolic alkalosis, its 24 to 36 hours, and the finding that neither hypoxaemia nor potassium depletion prevents it.
Worked examples
Each one runs through the calculator above, so the arithmetic here is the arithmetic it does.
Is pH 7.26 with a pCO2 of 60 and bicarbonate of 26 an acute or chronic respiratory acidosis?
- pH: 7.26, acidemia, so the pH is below the reference interval
- Primary: respiratory acidosis
- Compensation, acute: appropriate, expected 24.0 to 28.0 mmol/L HCO3, measured 26.0
- Compensation, chronic: insufficient, expected 30.0 to 34.0 mmol/L HCO3, measured 26.0
- Anion gap: 10.0, corrected to 10.0 mmol/L, which is normal
- Reading: single disorder
Acute. A bicarbonate of 26 fits the acute band of 24 to 28 and falls short of the chronic one, 30 to 34, each plus or minus 2 as Ayala-De la Cruz and colleagues apply the rules. The chronic band assumes the 3 to 5 days Merck Manual gives the kidneys to raise bicarbonate. That fits an opioid overdose, where Merck names respiratory depression as the main toxic effect.
What does a high delta ratio mean with sodium 136, chloride 90 and bicarbonate 16?
- pH: 7.32, acidemia, so the pH is below the reference interval
- Primary: metabolic acidosis
- Compensation: appropriate, expected 30.0 to 34.0 mmHg pCO2, measured 32.0
- Anion gap: 30.0, corrected to 30.0 mmol/L, which is raised
- Delta ratio: 2.25
- Reading: mixed disorder
A metabolic alkalosis on top, as in ketoacidosis with days of vomiting. The gap rose 18 while bicarbonate fell 8, and 16 + 18 is 34, above the normal range, which Merck reads as an alkalosis too. That alkalosis holds the pH at 7.32, above the 7.30 in Merck’s DKA criteria.
What pCO2 should a metabolic alkalosis with a bicarbonate of 34 have?
- pH: 7.48, alkalemia, so the pH is above the reference interval
- Primary: metabolic alkalosis
- Compensation: appropriate, expected 45.0 to 49.0 mmHg pCO2, measured 47.0
- Anion gap: 12.0, corrected to 12.0 mmol/L, which is normal
- Reading: single disorder
About 47 mmHg, in a band of 45 to 49 by the plus or minus 2 Ayala-De la Cruz and colleagues apply, so the high pCO2 is the lungs compensating and points to no second disorder. Merck gives 0.6 to 0.75 mmHg per mEq/L, up to about 55 mmHg, a cap the predicted 47 stays under, and lists loop and thiazide diuretics among the common causes.
Common questions
What order should I read a blood gas in?
Look at the pH first and name the disturbance as an acidemia or an alkalemia, or note that it is within range. Then decide whether the carbon dioxide or the bicarbonate explains it, which tells you whether the primary problem is respiratory or metabolic. Then check whether the compensation present is the amount expected, because compensation that falls short or overshoots means a second disorder is also running. Only then calculate the anion gap to narrow a metabolic acidosis. Doing it in this order is what stops a mixed disorder being read as a simple one.
Why does compensation never fully correct the pH?
Because the signal that drives compensation is the pH disturbance itself. If the pH returned exactly to normal the stimulus would be gone, so the response would stop, which means the body settles at a partial correction. The one recognized exception is long-standing respiratory alkalosis, as at high altitude or in pregnancy, where renal compensation can bring the pH back into the normal range. This is genuinely useful at the bedside: a pH that has returned all the way to the middle of the range in the presence of a large primary disturbance is evidence of a second, opposing disorder rather than of unusually effective compensation.
What is Winters’ formula for?
It predicts how far the carbon dioxide should fall in response to a metabolic acidosis: expected pCO2 is 1.5 times the bicarbonate plus 8, plus or minus 2, in mmHg. It answers a specific question, which is whether the respiratory response is appropriate. A measured pCO2 above the predicted range means there is a respiratory acidosis on top, and one below means a respiratory alkalosis is also present. It is a check on compensation, not a diagnosis, and it applies only to metabolic acidosis.
Why does the anion gap need correcting for albumin?
Because albumin is itself the largest contributor to the normal anion gap, carrying a net negative charge at physiological pH. In hypoalbuminemia the baseline gap is therefore lower, so a genuine raised-gap acidosis can present with a gap that looks normal. The usual correction adds about 2.5 mmol/L to the gap for every 1 g/dL that albumin falls below 4 g/dL. Missing this in a critically ill patient with a low albumin is one of the more common ways a lactic acidosis is overlooked.
Why do reference ranges here not match my hospital’s?
Because reference intervals depend on the analyser, the method and the population a laboratory derived them from, so they legitimately differ between institutions. The ranges used here are typical teaching values, chosen so the reasoning is easy to follow. When you interpret a real report, use the intervals printed on that report. The sequence of reasoning does not change, only the numbers you compare against.